


 download PDF

Introduction
Healthcare workers play a crucial role in strengthening health systems strengthening. Globally, health systems are facing significant challenges due to ongoing labour instability, driven by factors such as high work-related stress, stagnant income, critical skilled health worker shortages, and management-related challenges1,2. In low-and middle-income countries, especially in Sub-Saharan Africa, strikes often occur due to a shortage of healthcare workers, delayed pay, insufficient protective gear, and poor working conditions2, while in high-income countries unrest is attributed to chronic understaffing, declining income, and widespread burnout among healthcare workers1. This creates a situation of severe psychological distress because they can't provide the level of care they know is necessary due to barriers in the system1. Research from systematic reviews reveals that ongoing health workforce disputes resulting in protests depict fragile health systems that do not prioritize the wellbeing of healthcare workers providing healthcare services2. To avoid these issues and protect the healthcare workforce, it is crucial to prioritize the safety and wellbeing of health workers and ensure they receive adequate support. This approach not only upholds ethical labour practices but also protects public health and maintains continuous care1,2.
In Sub-Saharan Africa, the challenge is worsened by the dual issues of a high disease burden and a significant shortage of skilled healthcare personnel, impacting overall health outcomes3. As the UN Sustainable Development Goals target 2030, achieving Goal 3, which focuses on health for all at all ages, faces significant challenges. These include critical workforce shortages, especially in Sub-Saharan African nations, which need about 6.1 million skilled health workers by 2030 to meet population health needs4. Thus, prioritising the retention, enhancement, and wellbeing of the existing health workforce is essential for sustainable health system performance.
Wellbeing is a multidimensional concept encompassing physical, psychological, emotional, and social aspects of health. Positive wellbeing among health workers is associated with greater job satisfaction, motivation, and patient safety5. In contrast, poor wellbeing is associated with burnout, stress, and increased turnover intentions6. Healthcare workers, especially in rural areas, face compounding challenges such as high workloads due to staff shortages and greater burden of disease, inadequate medical supplies, limited infrastructure, weak managerial support, and insufficient remuneration, coupled with geographical aspects7.
In Kenya, approximately 69.1% of the total population resides in rural areas, where health indicators are worse than in urban areas8. Unfortunately, rural areas already face severe shortages of health personnel, and compromised wellbeing among health workers threatens service delivery and the continuity of care. Health workers in these regions encounter unique challenges, including high workloads, stock-outs of essential medications, and inadequate infrastructure9. While the devolution of health services has facilitated local governance, it has also resulted in delayed salaries, industrial unrest, and inconsistent human resource management, further impacting morale and wellbeing10.
Another major issue in Kenya is the recurrent and prolonged strikes by healthcare workers, reflecting significant discontentment and problems before and after the COVID-19 pandemic11-14. For instance, the 2017 public sector nurses' strike lasted 150 days12. The primary concerns driving these strikes include poor working conditions, inadequate infrastructure, lack of essential medical equipment, and delays in salary payments, sometimes lasting for months11-14. These issues worsen the existing shortage of skilled health professionals, compounded by brain drain, ultimately leading to poorer health outcomes for the population15.
The wellbeing of healthcare workers is crucial yet often neglected, as evidenced by the multiple challenges outlined above, underscoring the need for effective solutions. Therefore, this study aimed to address a knowledge gap by exploring the relationship between happiness, health status, and motivation of healthcare workers in a rural setting in the Republic of Kenya. The findings could inform the development of policies and interventions to promote health workforce wellbeing, which could ultimately enhance the quality of health service delivery and positive health outcomes for populations, especially for most of Kenya's population, which resides in rural areas.
Methods
Study design
Using a cross-sectional, quantitative study design, this study assessed the structural pathways affecting healthcare workforce wellbeing in Meru County, Kenya. Specifically, data collection was conducted among a sample of healthcare workers across all public and faith-based hospitals at the secondary and tertiary levels of care within the county, totalling 24 hospitals. In contrast to traditional unidirectional predictive models, this study implemented a non-recursive structural modelling approach16. This methodology effectively captures the bidirectional and continuous feedback loops that are fundamental to understanding workforce psychology16.
Study setting
In Kenyan rural areas, most hospitals are public (government-owned), followed by mission (not-for-profit or faith-based), then private-for-profit17. In Kenya, the health system is a devolved function, meaning there are various responsibilities between the one national government and 47 county semi-autonomous governments18. Ideally, the department of health in each county facilitates the implementation of existing national policy frameworks and regulations by effectively communicating and implementing strategic plans and programs in health facilities, such as hospitals19. The health system devolution has led to progress in the localisation of decision-making processes and improvements in the structural development of the health system at the county level18. However, devolving the Kenyan health system has presented additional challenges across each pillar due to the decentralisation of the health workforce, as was highlighted earlier, including inadequate human resources for health, poor distribution of the health workforce to rural areas, insufficient finances, and inadequate medical supplies18.
Sampling and sample size
A purposive sampling strategy was applied exclusively to healthcare professionals, given the research aim of understanding frontline health workers. The research required participants to have direct experience with the unique psychological, clinical, and operational aspects of care delivery on the front lines. By selecting participants based on their professional roles, the study accurately shows the impact of the variables examined, including real structural pressures such as working hours, the impact of patient care duties on healthcare workers' physical and psychological health, and organisational factors, which influence workplace happiness, motivation, and health-related quality of life (HRQoL).
Convenience sampling was used to select participants in the public and mission hospitals. Participation was open to all healthcare professionals who were willing to participate after receiving verbal and written information. The total number of participants in this study was 553.
Theoretical framework and hypothesis
The theoretical framework presented in this study challenges the traditional notion that factors such as health workforce happiness, motivation, and HRQoL operate in isolated, linear paths; instead, it posits that these elements interact within a dynamic feedback loop influenced by various factors.
In 2001, Fredrickson introduced the broaden-and-build theory, which explains that positive psychological assets – in this case, happiness – broaden a professional's cognitive scope, actively sparking motivation20. Increased motivation promotes professional efficacy, shielding health workers from occupational exhaustion and preserving their physical and mental HRQoL. Ultimately, a preserved baseline of the participants' overall health status serves as the physiological foundation for subjective happiness21.
The hypotheses evaluated in this study included:
- null hypothesis (H0): There is no significant interrelationship or structural feedback loop between happiness, work motivation, and HRQoL among healthcare workers in a rural area; the three constructs varied independently (γ=0)
- alternative hypothesis (H0): There is a significant positive and bidirectional interrelationship between happiness, work motivation, and HRQoL, forming a mutually reinforcing psychological feedback loop (γ≠0).
Data collection and data sources
Data collection took place between June and July 2020 in Meru County across all 24 public and mission (not-for-profit/faith-based) hospitals. Table 1 shows the variable descriptions, variable type, measurement tools, and attributes measured.
Table 1: Variable operationalisation and measurement tools22-24
| Variable | Variable type | Operationalised measurement tool | Key dimensions/attributes measured |
|---|---|---|---|
| Overall happiness | Endogenous predictor (independent variable) | Orientations to Happiness questionnaire22 | Measured overall happiness across three different orientations, namely through pleasure, through work engagement, and through meaning. Collectively, the scores add up to the final score on a scale of 18–90. |
| Overall work motivation | Endogenous predictor (Independent variable) | 23-item motivation self-administered questionnaire23 | Measured overall motivation, accounting for intrinsic and extrinsic motivation drivers, which together determine the overall level of motivation. Overall motivation was measured on a scale of 23–115. |
| Overall health-related quality of life | Endogenous outcomes (dependent variable) | EuroQol (EQ-5D) health-related quality of life questionnaire24 | Measured overall health status using the EQ Visual Analogue Scale on a scale of 0–100. |
| Exogenous covariates | Control variables (background factors) | Sociodemographic and occupational characteristics | Measured via sociodemographic section: age, marital status, monthly income level, total years of experience, professional cadre, and hospital type. |
Data analysis
Management of confounding variables
Cross-sectional data cannot experimentally manipulate exposures to produce cause-and-effect relationships; only correlations are possible. Therefore, identifying and controlling for confounding variables was critical to isolate the true pathways of healthcare workers' wellbeing. Sociodemographic and occupational characteristics, such as income, professional cadre, and facility type, can individually distort/skew baseline happiness data and health measures, leading to misleading correlations25.
Potential confounders were identified in systematic reviews on the three main constructs26,27. During the analysis, the change-in-estimate protocol was applied to include confirmed confounders as exogenous covariates in the final structural models. Bivariate associations between covariates and the primary constructs were tested. Any sociodemographic or occupational variable whose inclusion shifted the structural parameter estimates of the wellbeing triad by ≥10% was flagged as a confounding variable. To mitigate their impact, all confirmed confounders were incorporated as exogenous covariates in the final structural models, effectively partitioning their variance from the core wellbeing loops16.
Following this, the identified active confounders based on the empirical results of the 10% change-in-estimate protocol, professional cadre and income, which had a magnitude of shift of 11.23%, were explicitly added into the structural regression equations as control vectors. The results imply that when controlling for a particular professional cadre or income tier, the main path coefficient shifts by 11.23%. In a rural Kenyan healthcare setting, this makes perfect sense. A worker's professional tier fundamentally shifts both their baseline motivation levels (due to varying responsibilities/prestige/income) and their overall workplace happiness. Conversely, demographic factors such as sex (0.44%) and marital status (2.37%), as well as immediate institutional variables such as type of employment (0.17%) and recent in-service training (0.44%), were substantially below the conservative 10% change-in-estimate threshold. These parameters were therefore determined to be inactive confounders along the primary path, confirming that the core psychological feedback loop of mutual reinforcement operates independently of basic demographic traits across the surveyed workforce.
Therefore, the two variables professional cadre and income were included in the final three-stage least squares (3SLS) (reg3) regression models to ensure the structural paths were fully adjusted and accurate.
Based on the existing literature, there were exclusion restrictions on the variables, which were included in the regression model. The first exclusion restriction was the number of work hours per week. This variable is placed only in the overall health status equation (see ‘Regression analysis). It acts as an instrument that directly affects physical/somatic health through fatigue but only influences happiness or motivation through that channel. The second restriction was marital status, which was only in the overall motivation equation (see ‘Regression analysis’). This variable captures social support mechanisms outside of work that bolster personal drive, yet it does not have a direct effect on physical health outcomes or immediate job satisfaction.
Regression analysis
Data entry was done in Microsoft Excel and exported to STATA v15 (StataCorp; https://www.stata.com) for analysis. After data cleaning was completed, analysis was conducted in three phases.
Phase 1: Descriptive analysis
Descriptive analysis was conducted using measures of central tendency, such as mean, percentage, and range.
Phase 2: Bivariate covariation
A two-tailed Pearson correlation matrix (r) was computed across the total continuous scores of the three primary instruments, before controlling for confounders. This was conducted to establish the baseline strength, direction, and significance of the zero-order relationships before complex structural constraints were applied, at the p<0.05 significance level.
Phase 3: The three-stage least squares (reg3) regression model
Before analysis of specific structural pathways, global system diagnostics and goodness-of-fit metrics were conducted to ensure the mathematical soundness and stability of the 3SLS simultaneous equation framework (see descriptive statistics). The analysis relied on a clean, balanced dataset comprising 553 complete observations (N=553) across the three structural endpoints.
The 3SLS (reg3) regression model was used to analyse the cross-sectional data, accounting for active confounders. To evaluate the complete, non-recursive system of simultaneous equations, 3SLS regression modelling (reg3) was utilised. The use of 3SLS was preferred over ordinary least squares (OLS) because bidirectional feedback loops create endogeneity, which is prone to simultaneity bias. Using OLS estimation under endogeneity violates the assumption of independence, leading to biased and inconsistent coefficients. Therefore, the decision was made to use 3SLS to avoid this bias by using an instrumental variable approach, estimating all parameters concurrently while accounting for the correlated error terms across the three structural equations for each construct, as shown below.
Equation 1: Overall happiness:

Equation 2: Overall work motivation:

Equation 3: Overall health status:
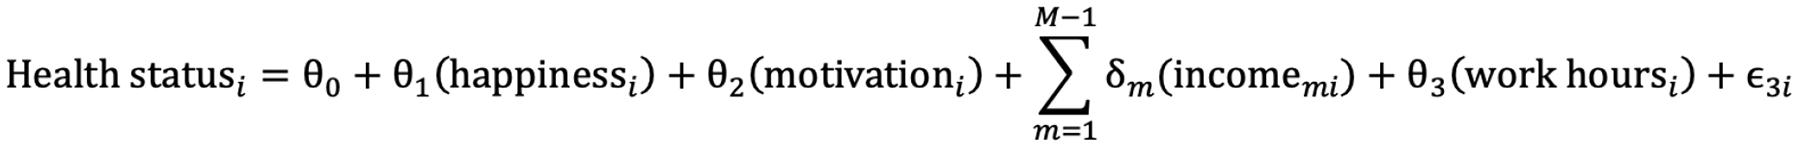
- β0, α0, θ0 represent the baseline intercepts.
- ∑γk and ∑δm represents the sets of coefficients for the dummy-coded categories of professional cadre and income, respectively.
- ε1i, ε2i and ε3i represent the structural disturbance terms (zetas), which allow correlation across equations.
Each equation considered different variables based on this study's results, such as linear correlations. However, exclusion restrictions are explicitly labelled ‘omitted restriction’ to indicate that the author deliberately omitted certain variables from specific equations to meet the order condition for structural equation identification, a vital rule in 3SLS.
Ethics approval
The University of Pretoria initially provided ethical approval of this study's protocol (718/2019). In Kenya, the institutional review board at the United States International University – Africa also approved the protocol for this study (USIU-A/IRB/130-2020). A national research licence (901924) was issued by the National Commission for Science, Technology and Innovation, Kenya. The Meru County Government Department of Health also permitted us to conduct this study in the county (CGM/COH/1/17(50)). Permission from all the hospital management teams was sought and received. Finally, informed consent forms were presented to all participants, who voluntarily signed them and then completed the survey. Universal anonymity was maintained by removing all personal identifiers from the dataset.
Results
Participant characteristics
Table 2 shows the characteristics of study participants.
Table 2: Participant characteristics (N=553)
| Variable | Category | n/mean±SD | %/min–max |
|---|---|---|---|
| Age | 36.52±9.54 | 20–78 | |
| Years of practice | 10.69±8.36 | 0–40 | |
| Work hours per week | 39.01±13.48 | 1–168 | |
| Hospital type | Public hospital | 434 | 78.48 |
| Mission hospital |
119 |
21.52 | |
| Type of employment | Full-time | 517 | 93.49 |
| Part-time |
36 |
6.51 | |
| Inservice training | Yes | 366 | 66.18 |
| No |
187 |
33.82 | |
| Staff housing | Yes | 74 | 13.38 |
| No |
479 |
86.62 | |
| Sex | Male | 213 | 38.52 |
| Female |
340 |
61.48 | |
| Marital status | Single | 179 | 32.37 |
| Married |
349 |
63.11 | |
| Widow |
25 |
4.52 | |
| Income tier (KES)† | 1: ≤15,999 | 25 | 4.52 |
| 2: 16,000–25,999 |
56 |
10.13 | |
| 3: 26,000–45,999 |
65 |
11.75 | |
| 4: 46,000–65,999 |
119 |
21.52 | |
| 5: 66,000–75,999 |
65 |
11.75 | |
| 6: 76,000–85,999 |
62 |
11.21 | |
| 7: 86,000–105,999 |
83 |
15.01 | |
| 8: ≥106,000 |
78 |
14.10 | |
| Professional cadre | Physician/doctor/medical officer | 28 | 5.06 |
| Nursing professional |
335 |
60.58 | |
| Dentistry professional or staff |
157 |
28.39 | |
| Pharmacy professional |
1 |
0.18 | |
| Clinical officer |
30 |
5.42 | |
| Medical laboratory scientist |
2 |
0.36 |
† KES1 = AUD0.0133, July 2020.
SD, standard deviation.
Descriptive statistics of primary variables
Table 3 data shows that the healthcare workforce exhibits a strong baseline in overall motivation (mean=88.64, standard deviation (SD)=12.70) and overall health status (mean=87.54, SD=10.61). However, there is a notable drop in their subjective workplace happiness, which shows a lower average (mean=64.58, SD=11.09) and a wider distribution. The motivation metrics further reveal significant variance in occupational motivation across the different healthcare professional cadres, with scores ranging from 20 to 100.
Table 3: Descriptive statistics and baseline distributions for the primary endogenous variables (N=553)
| Variable | Mean | Standard deviation | Minimum | Maximum |
|---|---|---|---|---|
| Overall happiness | 64.58 | 11.09 | 21 | 90 |
| Overall health status | 87.54 | 10.61 | 49 | 100 |
| Overall motivation | 88.64 | 12.70 | 20 | 100 |
Bivariate covariate results
The bivariate covariate results show that there is a moderate, positive, and highly statistically significant relationship between a healthcare worker's happiness and their motivation (p<0.001) (Table 4). As happiness increases, motivation tends to rise (and vice versa) (as shown in Table 4). There is a weak-to-moderate, positive, and highly significant linear relationship between motivation and health status (p<0.001). Healthcare workers with higher motivation generally report better health-related quality of life at a baseline, descriptive level. Finally, Table 4 shows there is a weaker, but still highly statistically significant (p=0.0003) positive relationship between overall happiness and overall health status.
Table 4 presents the bivariate results, examining only two variables at a time and without accounting for any additional factors. This underscores the need to employ the 3SLS model, which effectively illuminates the underlying mechanics by showing that the correlation between overall motivation and overall health disappears when controlling for very long working hours. In contrast, the relationship between overall happiness and overall motivation remains a significant driving force.
Table 4: Bivariate covariation results
| Overall happiness (p-value) | Overall motivation (p-value) | Overall health status | |
|---|---|---|---|
| Overall happiness | 1.0000 | ||
| Overall motivation | 0.3496*** (0.0000) | 1.0000 | |
| Overall health status | 0.1541*** (0.0003) | 0.2585*** (0.0000) | 1.0000 |
*p<0.05, **p<0.01, ***p<0.001
Global system diagnostics and goodness-of-fit
Because bivariate correlations fail to account for confounding influences, and ordinary linear frameworks suffer from simultaneity bias due to the bidirectional nature of workforce psychology, a 3SLS simultaneous equation model was deployed. Global system diagnostics and goodness-of-fit metrics were assessed to verify the model's mathematical stability (Table 5).
Table 5 summarises observations, parameter constraints, and goodness-of-fit for the wellbeing triad system. The global Wald χ2 tests for all three equations showed strong statistical significance (p<0.001), leading to a rejection of the null hypothesis that the independent variables produce no effect on the system endpoints (Table 5). Notably, the model exhibited strong explanatory power regarding the core wellbeing aspects of the triad, accounting for 20.76% of the overall variance in workforce motivation (χ2=144.92, p<0.001), and 15.05% of the variance in workplace happiness (χ2=97.95, p<0.001). For the third equation that assessed overall health status, a lower yet highly significant coefficient of determination (R2=53.26, p<0.001) was found. Overall, the root mean squared errors and significance thresholds indicate that the 3SLS framework is well specified, highly stable, and suitable for interpreting structural paths. This pattern aligns with human resources for health frameworks, which show that while workplace systems heavily shape motivation and job satisfaction, health status is primarily driven by individual and sociodemographic factors external to immediate occupational factors28,29.
Table 5: Global system diagnostics and goodness-of-fit metrics for the three-stage least squares simultaneous equation model (N=553)
| Variable | Parameters | Root mean squared error | R2 | χ2 | p-value |
|---|---|---|---|---|---|
| Overall happiness | 14 | 10.216 | 0.1505 | 97.95 | 0.0000 |
| Overall motivation | 17 | 9.443 | 0.2076 | 144.92 | 0.0000 |
| Overall health status | 10 | 12.120 | 0.0879 | 53.26 | 0.0000 |
Simultaneous equation structural parameters
Table 6 shows the results of the consolidated simultaneous equation structural parameters (3SLS system matrix) in relation to overall happiness, overall health status, and overall motivation among healthcare workers.
Overall happiness equation
In exploring the structural parameters within the 3SLS framework, we uncover the specific factors that influence workforce outcomes. The first equation that focuses on happiness identifies motivation as the leading contributor, with a coefficient of β=0.329 (95%CI 0.244–0.415, p<0.001) (Table 6). This means that, holding all socioeconomic and institutional factors constant, a one-unit increase in motivation corresponds to an increase of 0.329 units in overall happiness. On the other hand, overall health status shows no statistically significant direct effect on happiness by itself, as indicated by a coefficient of β=0.054 (p=0.131).
Among the institutional factors, a notable trend concerns professional hierarchy. Healthcare workers in the nursing professional cadre report significantly greater levels of happiness compared to those in the physician/doctor cadre, with a coefficient of β=4.225 (p=0.044); other cadres do not show any significant differences. Interestingly, none of the income levels from levels 2 to 8 (Table 6) reveal a direct significant effect on overall happiness (p>0.05). This suggests that, when adjusting for professional cadre and motivation, financial status alone does not guarantee higher happiness at work; rather, it is a combination of factors that matters.
Overall motivation equation
The second structural equation, which models overall motivation, highlights a strong bidirectional feedback loop between overall happiness and overall motivation. Table 6 shows that overall happiness significantly influences motivation, as evidenced by a coefficient of β=0.290 (95%CI 0.216–0.363, p<0.001), thus completing the cycle of wellbeing within the model. Additionally, overall health status emerges as a robust independent predictor of motivation, with a coefficient of β=0.184 (95%CI 0.120–0.247, p<0.001), underscoring the direct impact of physical wellbeing on work motivation.
While professional cadres do not seem to affect motivation scores significantly, the income control factors present an unexpected finding. Each upper-income tier (Table 6), starting from income tier 5, shows a statistically significant negative association when compared to the lowest-earning reference group (eg income tier 6: β=–7.440, p=0.002; income tier 8: β=–7.347, p=0.002). This indicates that healthcare workers in the top income levels report lower motivation than their lower-earning colleagues. Lastly, demographic data suggest that married healthcare workers demonstrate higher baseline motivation levels (β=6.881, p=0.013) than their single counterparts, suggesting the influence of social relationships on motivation.
Overall health status equation
The final structural equation maps the determinants of overall health status (HRQoL) within the simultaneous system. Table 6 shows that overall motivation serves as a powerful, highly significant protector of self-reported overall health status (β=0.299, 95%CI 0.196–0.402, p<0.001), validating that high internal professional resolve directly cushions healthcare workers against perceived physical or mental depletion. Conversely, happiness fails to reach the threshold for statistical significance (β=0.083, p=0.097), indicating that happiness does not directly improve baseline health status when motivation is controlled for.
Among the exogenous covariates, monthly income demonstrates a highly uniform, protective effect across the board. Compared to the lowest-earning benchmark (income tier 1; Table 6), nearly every upper-income tier reports significantly higher health status metrics (eg income tier 2: β=6.223, p=0.033; income tier 6: β=7.746, p=0.007; income tier 8: β=7.367, p=0.009). This starkly highlights that while higher income failed to increase overall happiness or overall motivation in previous equations, it serves as an indispensable material anchor for securing physical and health-related quality of life. Interestingly, in this system equation, self-reported weekly work hours do not exert a statistically significant independent direct effect on overall health status (β=0.024, p=0.528).
Table 6: Results of consolidated simultaneous equation structural parameters (three-stage least squares system matrix)
| Factor | Characteristic | Predictor variable | Equation 1: Overall happiness β (95%CI) | Equation 2: Overall motivation β (95%CI) | Equation 3: Overall health status β (95%CI) |
|---|---|---|---|---|---|
| Endogenous predictors | Overall happiness | –¶ | 0.290*** (0.216–0.363) | 0.083 (–0.015–0.182) | |
| Overall motivation | 0.329*** (0.244–0.415) | –¶ | 0.299*** (0.196–0.402) | ||
| Overall health status | 0.054 (–0.016–0.125) | 0.184*** (0.120–0.247) | –¶ | ||
| Occupational and demographic factors | Weekly work hours | –¶ | –¶ | 0.024 (–0.051–0.100) | |
| Professional cadre | Physician/doctor (ref.) | ||||
| Nursing professional |
4.225* (0.122–8.329) |
1.066 (–2.743–4.875) | –¶ | ||
| Dentistry professional or staff |
3.567 (–0.849–7.983) |
1.659 (–2.437–5.754) | –¶ | ||
| Pharmacy professional |
12.859 (–7.683–33.402) |
–1.832 (–20.857–17.194) | –¶ | ||
| Clinical officer |
2.378 (–3.536–8.291) |
4.150 (–1.312–9.613) | –¶ | ||
| Medical laboratory scientist |
1.435 (–13.566–16.436) |
6.768 (–7.093–20.629) | –¶ | ||
| Marital status | Single (ref.) | ||||
| Widow/widower |
–¶ |
4.834 (–0.770–10.437) | –¶ | ||
| Married |
–¶ |
6.881* (1.460–12.303) | –¶ | ||
| Socioeconomic factors | Income tier (KES)† | 1: ≤15,999) (ref.) | |||
| 2: 16,000–25,999 |
1.948 (–2.922–6.818) |
–2.752 (–7.257–1.753) | 6.223* (0.500–11.947) | ||
| 3: 26,000–45,999 |
0.219 (–4.528–4.966) |
–2.086 (–6.499–2.327) | 4.730 (–0.865–10.326) | ||
| 4: 46,000–65,999 |
–0.347 (–4.839–4.144) |
–2.691 (–6.889–1.506) | 6.066* (0.837–11.295) | ||
| 5: 66,000–75,999 |
–1.538 (–6.386–3.310) |
–5.251* (–9.851–0.651) | 6.815* (1.211–12.418) | ||
| 6: 76,000–85,999 |
0.433 (–4.467–5.333) |
–7.440** (–12.066–-2.813) | 7.746** (2.094–13.399) | ||
| 7: 86,000–105,999 |
–1.639 (–6.393–3.115) |
–6.230** (–10.751–1.709) | 6.591* (1.151–12.031) | ||
| 8: ≥106,000 |
–2.489 (–7.560–2.582) |
–7.347** (–12.099–2.595) | 7.367** (1.872–12.862) | ||
| Constant (α) | 27.784*** (18.303–37.264) | 54.632*** (46.819–62.446) | 49.972*** (39.134–60.811) |
*p<0.05, **p<0.01, ***p<0.001
† KES1 = AUD0.0133, July 2020.
¶ Omitted restriction.
CI, confidence interval.
Discussion
Key findings
This study utilises a 3SLS simultaneous equation model to map the structural dynamics of professional healthcare worker wellbeing, successfully addressing endogeneity and simultaneity biases. The empirical findings reject the null hypothesis across several core pathways, revealing a powerful, bidirectional feedback loop in which workplace happiness and motivation mutually reinforce one another among healthcare workers in a rural setting. Also, the study reveals that the baseline overall health status holds a highly significant, positive relationship with internal motivation. Crucially, the model unmasks a striking income paradox: upper-tier compensation brackets do not scale up occupational happiness and exhibit a significant negative relationship with motivation, supporting behavioural concepts of motivation crowding-out driven by escalating administrative burdens and scarce human and infrastructural resources. However, financial scaling cannot be minimised or dismissed, as the data show that income functions as an indispensable material shield that uniformly safeguards a clinician's physical health. In turn, baseline physical health serves as a foundational hygiene factor that directly fuels internal motivation, underscoring the need for health systems to protect the safety nets of the frontline workforce to enable them to thrive.
This study revealed that, among healthcare workers, happiness and motivation mutually reinforce one another, as evidenced by the positive correlation. A study conducted in Portugal involving 290 nurses revealed similar outcomes, demonstrating that those who feel motivated by a supportive work culture that fosters autonomy, meaningful feedback, and task-sharing tend to experience greater happiness in their roles30. Also, this study's findings align with the job demands–resources model proposed by Bakker and Demerouti in 2017, which highlights that when a hospital fosters a supportive atmosphere, it initiates a ‘motivational process’ that consistently generates long-term energy and commitment31. The results of this study show that, according to Fredrickson's broaden-and-build theory, positive emotions at work not only broaden a person's mental resilience but also naturally fuel their internal motivation over time20.
This study emphasises the critical role of both financial and non-financial incentives in fostering a motivated and satisfied health workforce. Research in the Netherlands highlights how income stability influences nurse retention, while job content fuels motivation32. Researchers have discovered that raising financial incentives alone isn't enough; they must also enhance workplace autonomy, task sharing, manageable workloads, and recognition, among other non-financial techniques, to keep healthcare workers passionate about patient care. This highlights the idea of performance-based financing, which past studies have indicated can boost motivation among healthcare workers in Malawi33,34. Additionally, studies indicate that higher salaries in senior clinical roles often come with burdensome responsibilities, contributing to burnout, underscoring the need for a balance between financial remuneration and meaningful work experiences21.
A significant discovery from this study indicates a strong correlation between income levels and overall health among healthcare workers; those with higher earnings reported better health. Similarly, a study conducted in Türkiye among healthcare professionals found that greater happiness helps mitigate burnout and depression, ultimately enhancing the quality of patient care35, underscoring the importance of these findings. These conclusions are consistent with global public health guidelines, which point out that a fair salary provides an essential foundation for healthcare workers, enabling them to afford adequate nutrition, secure housing, and necessary personal health care29.
The current research highlights that when healthcare workers face physical and mental fatigue, indicated by a decline in their health status, their motivation tends to decrease. A study in Italy among 656 healthcare professionals revealed that heavy workload, such as working as a nurse or midwife, significantly increased depressive risks and reduced satisfaction, while operating in intensive care or surgery damaged general health36. Previous studies revealed that while management can effectively influence a worker's psychological state, a person's physical capabilities are fundamentally determined by biomedical factors28. When a health system neglects to safeguard its clinicians against basic physical exhaustion, it undermines the foundation essential to maintaining a strong internal work ethic.
Limitations
The study acknowledges several limitations that warrant attention in future research. Primarily, its reliance on cross-sectional data restricts the analysis to correlational insights rather than establishing cause-and-effect dynamics. While the 3SLS simultaneous architecture adeptly addresses endogeneity and articulates structural relationships within the identified wellbeing triad, establishing true temporal causality requires experimental or longitudinal data that track changes in healthcare workers' experiences over time. Furthermore, no model can encompass all relevant variables, underscoring the need for additional studies to explore similarities and differences in healthcare workers’ wellbeing, which remains a global priority for workforce strengthening.
The study focused on healthcare workers with clinical training in public and mission hospitals at the secondary and tertiary levels, highlighting the limitations of this narrower scope. Future research should expand to encompass community health workers, non-clinical roles, and private healthcare facilities. Given the rural Kenyan context of this study, findings may resonate with similar rural settings globally. However, there is a pressing need for additional studies to deepen the understanding of the wellbeing triad across various geographic contexts worldwide, enabling comparative analyses to address this critical global concern. It's also worth noting that psychological and emotional assessments can be subjective and less reliable than physical measures, which complicates their interpretation. This cross-sectional study primarily relied on quantitative data. It did not focus on qualitative data that capture lived experiences and offer insights into healthcare workers’ happiness, health, and motivation, as these aspects of wellbeing had already been explored qualitatively in Kenya before this study21. However, this is not the case in other countries; thus, for comparative purposes, mixed-methods research on healthcare workers' wellbeing could build on this study's findings.
Policy implications
This study reveals findings that could be insightful for health facility managers, ministries of health, and health policymakers in countries that are aiming to enhance and prioritise healthcare workers’ wellbeing. Specifically, this study shows that health system strengthening, especially in rural settings, requires policy architects to transition toward strategic work design, including actively enhancing clinical autonomy, optimising scheduling, and minimising bureaucratic workloads, while simultaneously securing an adequate and competitive living-wage baseline to protect the overall health of the health workforce as they provide health care services.
Additionally, the results show that it is paramount to aim at a balance between financial and non-financial incentives when reassessing the weight of monetary rewards in motivating employees, which should be considered by policymakers and health facility administrators. Non-financial incentives, such as opportunities for career advancement and a supportive work environment, are crucial for fostering healthcare worker wellbeing. Therefore, retention and productivity strategies must integrate both monetary and non-monetary rewards to cultivate a positive workplace culture and enhance service delivery.
Health administrators, policymakers and implementers alike must prioritise funding for workplace and psychological support to enhance healthcare workers' wellbeing. This study underscores the importance of addressing the wellbeing triad including happiness, motivation, and health-related quality of life, as vital strategies for effective policymaking. Specifically, policies need to mandate manageable weekly work hours, flexible scheduling, active peer support groups, and clinical safety protections. Safeguarding the physical and emotional workspace prevents the negative emotions that diminish satisfaction, ensuring that the self-charging battery of worker wellbeing remains active.
Conclusion
This study demonstrates that work-related happiness, motivation, and health-related quality of life among healthcare workers do not exist in isolation but function as a dynamic, non-recursive psychological ecosystem. By rejecting a conventional linear cause-and-effect approach and utilising a 3SLS model structural framework, the analysis confirmed that subjective happiness and workforce motivation operate within a mutually reinforcing feedback loop that directly preserves frontline physical and mental health. The 3SLS structural model reveals that happiness serves as a strong protective factor for healthcare workers' HRQoL and work motivation. In fact, significant operational demands, such as long work hours, can seriously undermine overall health status. Therefore, depending solely on professional calling or motivation is an unfeasible strategy that risks overwhelming burnout and other negative health outcomes.
To strengthen healthcare systems, policy- and decision-makers must transition from reactive management to proactive, human-focused strategies. Ideally, this involves going beyond strict output goals to implement firm limits on weekly work hours, ensure adequate and timely compensation or income, prioritise HRQoL for healthcare workers, and create nurturing workplace environments that sustain the essential engine of workforce motivation.
Acknowledgements
I would like to thank the study participants for consenting to participate in this study.
Funding
No funding was received for this study.
Conflicts of interest
The author declares no conflict of interest.
AI disclosure statement
The author used standard Grammarly v1.2.235, only for basic grammar and spelling checks during the preparation of this manuscript. The author has reviewed and takes full responsibility for the final content, accuracy, and integrity of the published manuscript.
Data availability
The study materials and data can be made available upon request to the corresponding author.